Nasal Steroid Spray Long-Term Effects on Airway Function
Steroid sprays suppress allergy symptoms but never fix the immune dysfunction driving them.
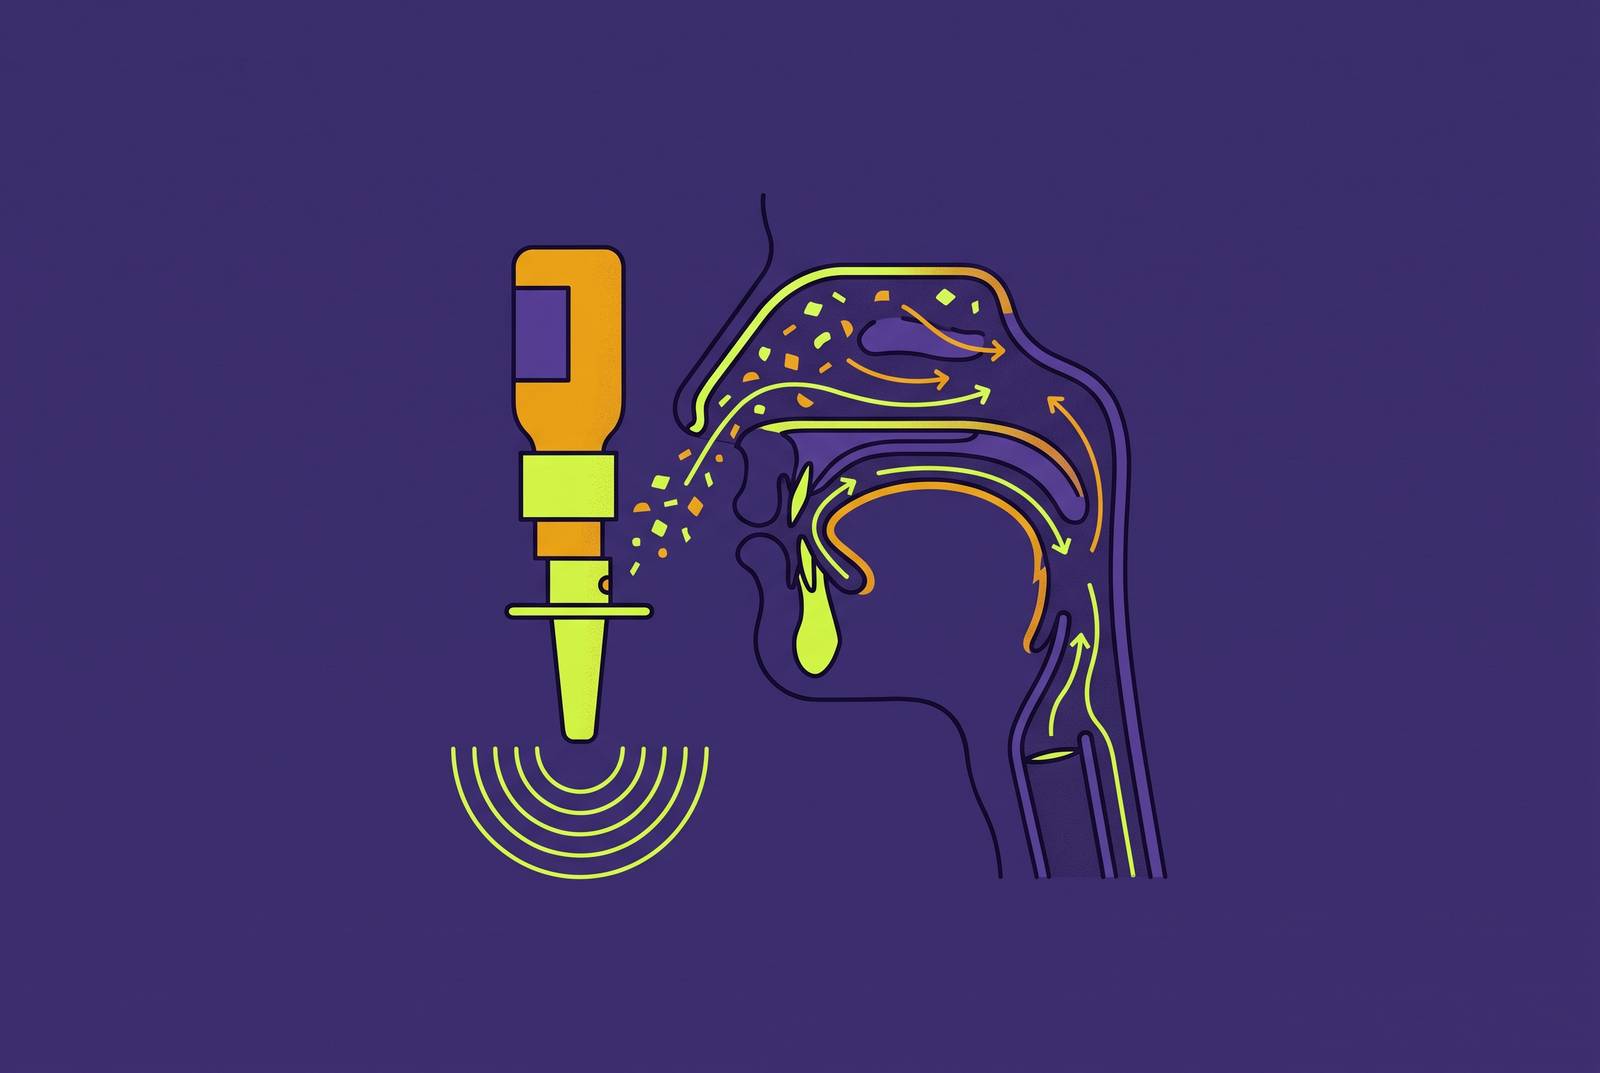
Nasal steroid sprays are widely considered safe for long-term use, but they manage inflammation without correcting the immune dysfunction driving it, so the airway never fully normalizes for allergy sufferers who rely on them indefinitely. These sprays suppress the local inflammatory response that allergens trigger: they calm swelling, cut mucus production, and dial down histamine release in the nasal lining. What they do not do is touch the reason that inflammation started in the first place. The immune system's IgE-mediated reaction, the actual allergic trigger, keeps firing underneath the spray. Think of it as turning down the volume on an alarm that keeps ringing, rather than finding out why it went off.
That gap matters once you notice how the sprays behave in real time. They're slow. This is a drug built for anticipation, not rescue, one that has to run continuously because the trigger driving the reaction never goes away on its own.
Two other nasal sprays people tend to lump in with steroid sprays work nothing alike. Decongestant sprays (oxymetazoline, xylometazoline) shrink blood vessels directly, and they carry a very different risk, covered later in this piece. Antihistamine nasal sprays (azelastine, olopatadine) block histamine receptors and bring some anti-inflammatory, mast-cell-stabilizing effect of their own, with a separate side-effect profile. None of this is a knock against corticosteroid sprays. They're the recognized first-line therapy for both allergic and non-allergic rhinitis, and that's the clinical starting point this piece works from, not the thing it's trying to overturn.
How bioavailability determines how much of the drug enters the bloodstream
For anyone using these sprays for years rather than weeks, the single most important number is bioavailability: how much of the drug leaves the nose and enters general circulation. A spray that stays local carries a fundamentally different risk profile than one that migrates into the bloodstream, and that number swings wildly by formulation.
Triamcinolone acetonide (sold as Nasocort) runs at 46% systemic bioavailability. Beclometasone dipropionate (Beconase) is 44%, and budesonide (Rhinocort Aqua) is 31%. Compare that to fluticasone propionate (Flixonase or Nasofan), at 0.42%, mometasone furoate (Nasonex), at 0.46%, or the fluticasone-azelastine combination (Dymista), at 1.86% bsaci.org. That's the difference between a formulation where less than half a percent of the dose reaches the bloodstream and one where nearly half of it does.
Cleveland Clinic Journal of Medicine guidance from Dr. Lily C. Pien backs up with Cleveland Clinic Journal of Medicine guidance: long-term nasal steroid use is genuinely safe, but anyone facing continuous, extended treatment should be on a formulation with low systemic bioavailability. One is on fluticasone, one is on triamcinolone. Their day-to-day symptom relief might look identical. Their systemic exposure over a decade does not. Most patients couldn't tell you which formulation they're on if you asked, let alone what the bioavailability number means for them. That's not a small oversight, given how much it should shape the conversation with whoever's prescribing it.
What the evidence shows about local tissue effects with extended use
Start with the reassuring part, because there is one. Mucosal atrophy, thinning of the nasal lining tissue, has not shown up in studies of fluticasone or mometasone use running a full year, or with budesonide use tracked out to 5.5 years. For the low-bioavailability formulations used properly, that's about as clean a long-term safety signal as you'll find for a daily medication.
That doesn't mean nothing happens locally. Burning, dryness, crusting, and the occasional nosebleed appear consistently in both the Cleveland Clinic guidance and the BSACI protocol. Rarer, and more serious: septal perforations, actual holes in the wall of tissue dividing the nostrils. These occur most often in the first year of use, and they track closely with incorrect spray technique, specifically aiming the nozzle at the septum instead of angling away from it. Which raises a fair question: how many of these injuries are really about the drug, versus about nobody ever showing the patient the right angle to hold the bottle? The BSACI protocol is explicit about this, spelling out angle and hand-crossing technique (using the right hand for the left nostril and vice versa, which naturally angles the spray outward) specifically to cut this risk down. It's a structural detail, buried in a pamphlet nobody reads, that determines whether the tissue holds up over years of use. Anyone on long-term therapy should also have the nasal cavity examined at least once a year, Cleveland Clinic Journal of Medicine advises, a cheap habit against a rare but real risk.
The bigger fear patients sometimes bring up, glaucoma and cataracts from steroid exposure, doesn't hold up under the data available. Two large studies, one case-control study of roughly 1,997 cases and one retrospective study covering more than 286,000 patients, found no association between intranasal steroid use and either condition. What's still an open question is what happens when someone combines long-term nasal steroids with inhaled corticosteroids for asthma, since a fair number of allergy patients are managing both conditions at once. The Cleveland Clinic guidance flags this combined exposure as genuinely understudied, even if it isn't cause for alarm on its own.
Children and long-term nasal steroid use: where the safety picture is less settled
Adults get a fairly clean bill of health on low-bioavailability formulations. Children are a different conversation, and growth is the reason why. Beclomethasone dipropionate, used for a full year, has been shown to measurably affect children's growth. That's not a theoretical risk buried in a footnote; it's a documented effect tied to a specific formulation and duration.
Fluticasone and mometasone haven't shown that same growth effect, and both are FDA-approved for young children, making them the preferred choices in pediatric cases. Triamcinolone acetonide carries its own explicit restriction in the BSACI protocol: it shouldn't be used for longer than 12 months in children under 12 South Valley Ear Nose & Throat - Nasal Spray Long-Term Use. So the formulation choice that mattered for bioavailability reasons in adults matters even more here, for a completely different reason. Children on any steroid nasal spray should be under a physician's guidance with growth tracked regularly, and Cleveland Clinic Journal of Medicine points toward newer-generation formulations at low doses as the sensible default for this age group.
But withholding treatment isn't a neutral choice either. The BSACI notes that properly treating rhinitis in children can improve cognitive function and cut down on days missed from school. So under-treating a child's allergies to avoid growth risk trades one cost for another: fewer physical side effects, maybe, but worse concentration, worse sleep, more missed classroom time. None of this means nasal steroids are unsafe for kids. It means the blanket reassurance that adults get, "long-term use is fine," needs a footnote for pediatric cases that adults' own treatment conversations don't require.
The problem nasal steroids are managing but not solving: what happens to the airway when treatment is continuous but the allergy persists
Here the central tension of this whole subject becomes clear. The BSACI standard operating procedure states that perennial allergens, house dust mite being the clearest example, are more likely to demand continuous, indefinite treatment. For a lot of allergy sufferers, that's a permanent condition, indefinitely.
So what actually happens over that stretch of years? The spray keeps suppressing inflammation in the nasal lining. Meanwhile, the immune system keeps mounting the exact same IgE-driven response to the exact same triggers, underneath the suppression, and if the spray stops, symptoms tend to come right back, often within days. The airway is being managed. It is not being reprogrammed, and that distinction is the whole argument.
What does incomplete management actually cost someone day to day? Nasal blockage that isn't fully resolved leads to mouth breathing, snoring, and fragmented sleep. Data cited from a Sleep Foundation source found that people with untreated allergic rhinitis wake up more often at night and get less deep sleep than people without it. The BSACI itself lists improved sleep quality and sharper cognitive function among the real benefits of properly treating rhinitis, which cuts the other way too: partial or inadequate control leaves those same deficits sitting there, unaddressed, night after night.
These sprays are not built to handle certain things. Inhaled corticosteroid nasal sprays don't reduce inflammation from acute viral infections, atrophic rhinitis, vasomotor rhinitis, or hormonally driven vasomotor instability. Their effectiveness is specific to allergic and certain non-allergic forms of rhinitis, so the airway isn't broadly shielded just because someone's using the spray daily. "Long-term safe" and "restores full airway function" sound like they should mean the same thing. The evidence backs the first claim solidly. It does not back the second, not for someone dealing with a perennial allergen that never actually leaves the environment.
Why decongestant spray overuse causes a separate, more damaging airway problem
Decongestant sprays deserve their own section because conflating them with steroid sprays leads to real confusion, and real harm. Rhinitis medicamentosa, rebound congestion from extended decongestant use (oxymetazoline, xylometazoline), is a completely separate condition from anything a corticosteroid spray produces.
The mechanism is mechanical, almost literally. Blood vessels in the nasal lining constrict when the drug hits them, then rebound and swell even worse once the drug wears off. Repeat that cycle daily and the tissue itself starts depending on the spray just to stay open at all. WebMD/Wang, MD, states that this cycle can continue for months, years, and even decades, and long-term use can lead to chronic sinusitis, permanent tissue swelling, infection, and pain. That's a materially different, and arguably harsher, outcome than anything documented for steroid sprays used correctly.
The guideline from the American Academy of Asthma, Allergy, and Immunology is specific: decongestant sprays shouldn't be used more than twice a day for more than 3 days South Valley Ear Nose & Throat - Nasal Spray Long-Term Use. Three days. Not three weeks. Getting out of rhinitis medicamentosa once it's set in requires stopping the spray completely, and because the rebound congestion can be severe, physicians sometimes prescribe a short course of oral steroids just to get someone through withdrawal. A recent clinical trial cited in Wikipedia found that a corticosteroid nasal spray may actually help reverse rhinitis medicamentosa, and the same drug class this piece has spent several sections holding to a high standard turns out to be part of the fix for a completely different spray's damage.
How do you tell the two apart in practice? Rhinitis medicamentosa tends to appear as congestion alone, without the eye itching or sneezing that usually rides along with allergy. It doesn't follow a seasonal pattern, and it tends to get worse the more the spray gets used, not better. If that sounds familiar to someone reaching for an over-the-counter decongestant, that's worth a conversation with a doctor, not another spray.
What symptom control leaves unaddressed: the immune system is still reacting to the same triggers
Histamine isn't just an allergy chemical. It works as a neurotransmitter, helping regulate alertness and sleep cycles, so when allergic inflammation keeps disrupting histamine balance and cytokine signaling over time, energy and mental sharpness take a hit, even in someone whose nasal symptoms are mostly under control.
Why would partial control still cost someone cognitively? The brain uses something like a fifth of the body's total oxygen supply, despite being a small fraction of total body weight, so even a modest dip in breathing efficiency, the kind that lingers after "pretty good" symptom control, can appear as noticeable fog. A child on a steroid spray that's working reasonably well might still struggle to concentrate in class or sleep through the night. A working adult might still feel that seasonal mental drain every spring. Not because the spray failed at its job, but because "controlled inflammation" and "no inflammation" are not the same physiological state, even when the difference is subtle enough to miss.
The actual machinery driving the allergic response, IgE sensitization, mast cells primed and ready to fire, keeps running regardless of how well the mucosal surface looks on any given day, producing symptoms independent of surface appearance. The spray leaves all of that untrained. That's the structural gap running through this entire piece: the medication treats the symptom's expression. The sensitization generating that symptom sits untouched, and can, over years, actually broaden as someone gets exposed to new allergens.
What immunotherapy does differently: modifying the immune response rather than suppressing its output
Sublingual immunotherapy (SLIT) takes a different approach entirely. It works by giving repeated small doses of an allergen under the tongue, gradually reducing the immune system's sensitivity to that specific trigger. Instead of managing the inflammation an allergic reaction produces, it targets the IgE-mediated response causing the reaction in the first place, which is the gap steroid sprays leave open.
Recent research has strengthened the evidence behind this. A 2025 meta-analysis confirmed the clinical effectiveness and safety of index-of-reactivity liquid SLIT for allergic rhinoconjunctivitis, holding up across allergens and age groups, with low rates of adverse events and strong patient adherence. Multiple meta-analyses beyond that one show SLIT meaningfully cuts both clinical symptoms and the amount of anti-allergic medication patients need going forward, meaning people who finish a course of treatment often need less spray, or none, afterward. That's a fundamentally different outcome than "keep using this indefinitely."
There's a concept researchers call the "unified airway", the idea that the nose, sinuses, and throat function as one connected system rather than separate parts. One study tracking this over three years found improvement in both pharyngeal and nasal symptoms, along with reduced medication use and better quality of life, and that broader improvement occurs because the treatment addresses the immune driver behind the reaction, not just the surface tissue reacting to it. On safety, the systematic review literature on SLIT describes it as largely free from serious systemic reactions, which matters because anaphylaxis, the main risk tied to subcutaneous allergy injections, isn't a meaningful concern with a sublingual approach.
The pediatric data has moved forward too. A 2025 Phase III trial published in Allergy found the SQ tree sublingual immunotherapy tablet effective and well tolerated in children, which lands directly on the population where long-term steroid spray use carries the most open questions. A separate 2025 Phase III randomized trial, also in Allergy, studied the SQ house dust mite tablet in children with allergic asthma, tackling exactly the perennial-allergen, continuous-treatment population this piece has been circling back to since the section on airway function.
How to think about nasal steroid sprays in a broader allergy management picture
None of this makes nasal steroid sprays the wrong tool. They're well-suited to managing symptoms during high-exposure stretches, useful as a bridge while immunotherapy builds toward its own effect, and often the right call for patients who aren't good candidates for immunotherapy at all.
Where they fall short is as a permanent solution for someone facing a perennial allergen that never lets up. Using the spray indefinitely keeps the airway managed. It does not normalize the immune function generating the reaction underneath: a spray that works exactly as intended, used exactly as directed, on the right low-bioavailability formulation, is still not the same thing as an immune system that's learned to stop overreacting. One controls the weather. The other changes the climate. Anyone facing years, not weeks, of treatment should have that exact conversation with a doctor: is this spray managing things while something else does the deeper work, or is it the only plan on the table? SOURCE PAGES (what the pages behind the outline's links say).